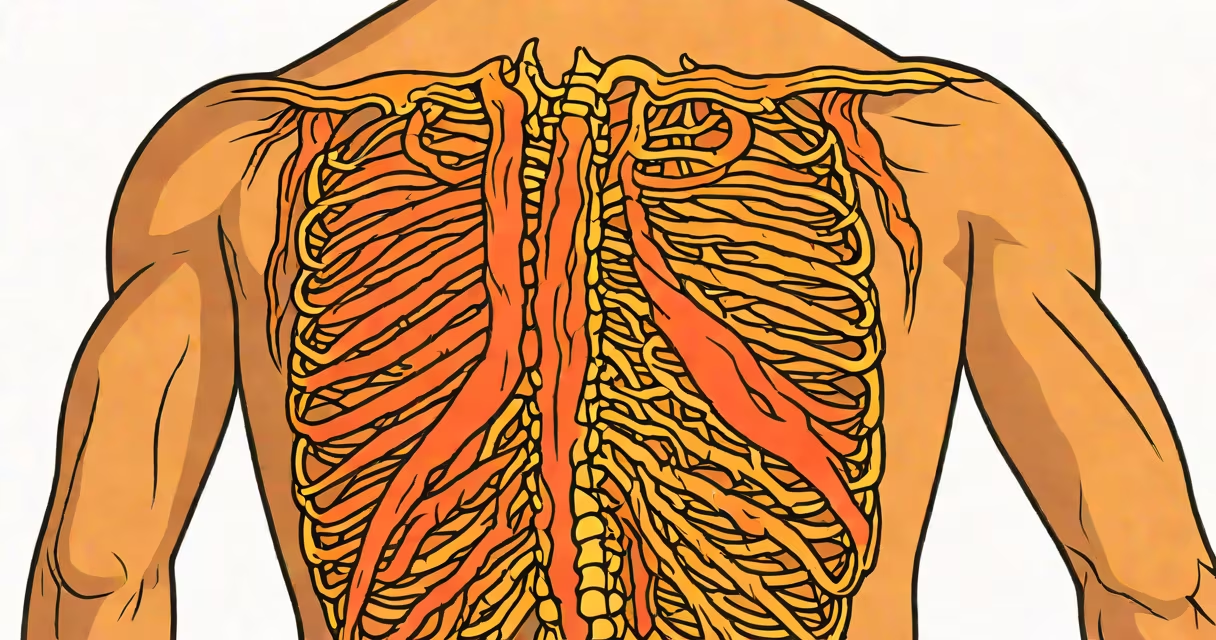
Chest pain in ribs and back refers to discomfort localized along the ribcage and extending into the upper or mid-back, often caused by musculoskeletal issues, nerve irritation, or referred pain from internal organs. It may feel sharp, dull, or pressure-like and typically worsens with movement, breathing, or posture changes.
This pain arises from structures including the thoracic vertebrae, intercostal muscles, costovertebral joints, and surrounding nerves. Common triggers include sudden twisting motions, heavy lifting, poor posture, or trauma. While often benign, persistent or severe symptoms require medical evaluation to rule out cardiac, pulmonary, or gastrointestinal origins.
The rib cage spans 12 pairs of ribs attached to the thoracic spine posteriorly and the sternum anteriorly. Between each rib lies an intercostal muscle group responsible for stabilizing the chest wall during respiration. Nerves exit the spinal column at each thoracic level and run beneath the ribs, forming the intercostal nerve network.
Pain in this region typically results from mechanical stress on these tissues. For example, a sudden twist while lifting weights can strain the intercostal muscles or irritate the costovertebral joints where ribs meet the spine. This leads to localized tenderness, sharp pain with deep breaths, or pain that radiates around the torso.
A 2021 study in Spine Journal found that 68% of patients presenting with upper back and rib pain had musculoskeletal etiologies, with only 5% linked to internal organ pathology. This highlights that most cases are not life-threatening but still require accurate diagnosis to avoid mismanagement.
Not all chest pain in ribs and back stems from the same source. The primary categories include musculoskeletal, visceral (organ-related), and neurological causes.
| Type | Key Features | Common Triggers | Typical Duration |
|---|---|---|---|
| Musculoskeletal | Sharp, localized pain; worsens with movement or palpation | Twisting, lifting, poor posture | Days to weeks |
| Visceral (referred) | Dull, aching; may radiate to shoulder or arm | Gallbladder attacks, pancreatitis, kidney stones | Episodic, often with other symptoms |
| Neurological | Burning, tingling; follows a dermatomal pattern | Shingles (herpes zoster), nerve compression | Weeks to months |
Costochondritis- inflammation of the cartilage connecting ribs to the sternum-is a frequent cause of sharp, reproducible pain in the front and side of the chest. A 2019 review in Journal of Family Practice noted that it accounts for 10-20% of non-cardiac chest pain cases in outpatient settings.
One non-obvious distinction: pain from shingles often appears unilaterally, following a band-like path along a single rib level. It may precede the rash by days, making early recognition critical. Misdiagnosing it as musculoskeletal strain delays antiviral treatment and increases risk of post-herpetic neuralgia.
While musculoskeletal causes dominate, chest pain in ribs and back can signal serious conditions. Cardiac ischemia may present with atypical pain patterns, especially in women and older adults. Pain may localize to the left side of the chest, radiate to the back, and occur during exertion or rest.
Pulmonary embolism-a blood clot in the lung-can mimic rib pain. Symptoms include sudden onset of sharp, pleuritic pain (worsened by breathing), shortness of breath, and rapid heart rate. The American Heart Association notes that up to 30% of PE cases initially present with back or chest pain without classic respiratory signs.
Referred pain from abdominal organs is less obvious. For example, gallstones can cause pain under the right rib cage that radiates to the back between the shoulder blades. A 2020 study in Annals of Internal Medicine found that 44% of patients with acute cholecystitis reported back pain as a primary symptom.
As a clinician, I've seen patients misattribute flank pain to "bad posture" until imaging revealed a 1.2 cm kidney stone causing obstruction. The pain was felt in the lower back and radiated forward-mimicking mechanical strain. This underscores the need for differential diagnosis beyond surface-level assessment.
Immediate medical attention is needed if chest pain in ribs and back is accompanied by:
These signs may indicate aortic dissection, myocardial infarction, or malignancy. The CDC emphasizes that delayed care for heart attacks increases mortality by 25% in individuals over 65.
If pain persists beyond a week with no improvement, or worsens with activity, consult a healthcare provider. Diagnostic tools such as X-rays, CT scans, or MRI may be used to assess bone integrity, soft tissue injury, or internal abnormalities.
Many assume that any chest pain must be heart-related. However, the National Institute of Health reports that only 15-20% of emergency department visits for chest pain involve cardiac causes. Most are musculoskeletal, anxiety-related, or gastrointestinal.
Another misconception: back pain from ribs is always due to poor posture. While posture plays a role, repetitive strain injuries-such as those from prolonged computer use-are often overlooked. A 2022 study in Occupational Medicine found that office workers with sedentary habits were 3.4 times more likely to report thoracic back pain than those who took regular movement breaks.
Some confuse gas pain chest back with structural issues. Gas trapped in the digestive tract can press against the diaphragm and create sharp, shifting pain near the ribs and upper back. This pain often improves after burping or passing gas. If you suspect gas-related discomfort, a short guide on identifying gas pain can help differentiate it from musculoskeletal or cardiac causes.
Consider a 42-year-old woman reporting sharp pain on her left side, between the 6th and 8th ribs, that worsens when she turns in bed. She denies trauma, fever, or shortness of breath. On exam, the area is tender to touch, and pain increases with deep inhalation.
Given the location and reproducibility, costochondritis is likely. Imaging is not required unless symptoms persist past two weeks. Treatment includes NSAIDs, heat application, and avoiding movements that exacerbate pain. Recovery typically occurs within 4-6 weeks.
In contrast, if the same patient reported sudden onset of tearing pain radiating from the chest to the back, with elevated blood pressure, a CT angiogram would be indicated to rule out aortic dissection.
Chest pain in ribs and back is frequently musculoskeletal, arising from strained muscles, inflamed joints, or nerve irritation. It often resolves with rest, anti-inflammatory medication, and posture correction. However, it can also signal serious underlying conditions requiring prompt evaluation.
Always consider red flags: sudden severity, radiation to arms or jaw, associated shortness of breath, or neurological deficits. If symptoms persist or worsen, seek medical advice. Understanding the origin prevents unnecessary tests and ensures timely intervention.